Subglottic Hemangioma: Symptoms, Diagnosis & Treatment
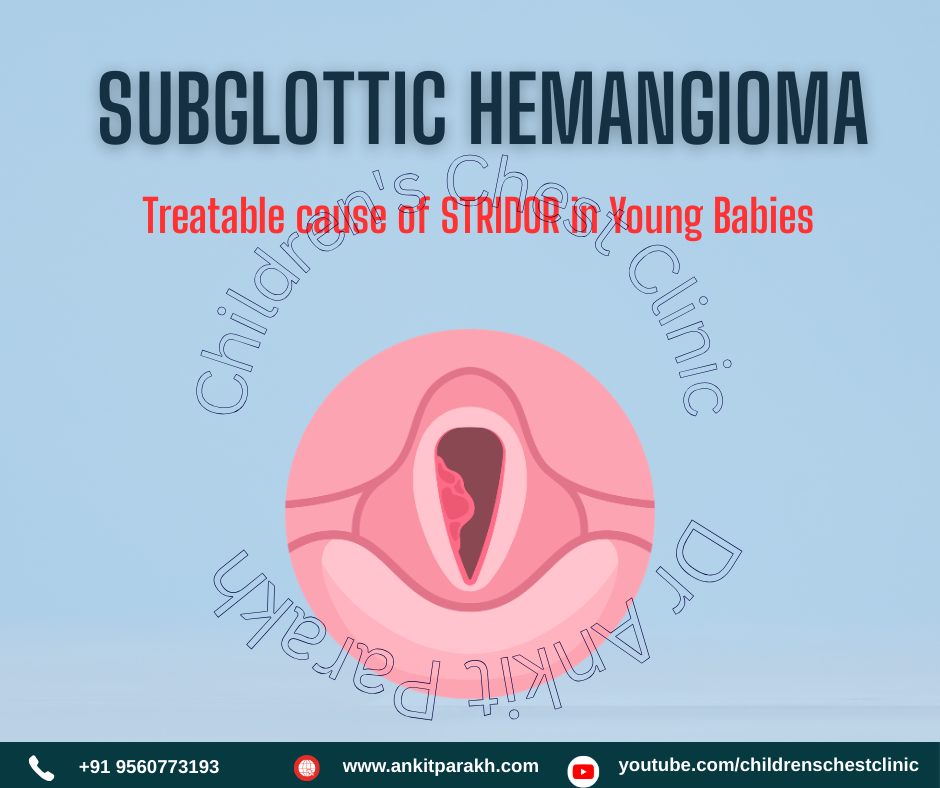
Subglottic Hemangioma is a rare but potentially serious cause of airway obstruction in infants. It is a type of benign vascular tumor that develops just below the vocal cords (subglottic region) and can significantly affect breathing as it grows.
Because early symptoms may mimic more common conditions, awareness of Subglottic Hemangioma is crucial for timely diagnosis and management. In this article, we focus on presenting symptoms, the role of bronchoscopy in diagnosis, and current treatment approaches.
What is a Subglottic Hemangioma?
A Subglottic Hemangioma is a collection of abnormal blood vessels that forms in the airway below the vocal cords. These lesions typically:
- Are not always present at birth but develop within the first few weeks of life
- Grow rapidly during infancy (proliferative phase)
- Gradually shrink over time (involution phase)
However, during the growth phase, they can cause significant airway narrowing.
Presenting Symptoms of Subglottic Hemangioma
The hallmark symptom is stridor, but the pattern and progression are key clues.
1. Biphasic Stridor (Key Feature)
- Stridor is typically biphasic (heard during both inspiration and expiration)
- Progressive in nature
- Often begins between 2 to 8 weeks of age
2. Worsening Breathing Difficulty
- Increasing noisy breathing over days to weeks
- May initially be mild but progressively worsens
3. Recurrent or Persistent “Croup-like” Symptoms
- Frequent episodes diagnosed as croup
- Poor or temporary response to standard croup treatments
4. Respiratory Distress
- Chest retractions
- Rapid breathing
- Nasal flaring
- Cyanosis in critical obstruction
5. Feeding Difficulties
- Difficulty feeding due to breathing issues
- Poor weight gain in prolonged cases
6. Associated Skin Hemangiomas
- Presence of cutaneous hemangiomas, especially in a “beard distribution” (around chin, neck, lower face)
When to Suspect Subglottic Hemangioma?
- Progressive stridor starting after a few weeks of life
- Recurrent croup-like episodes
- Poor response to routine treatments
- Associated skin hemangiomas
Investigations: Confirming the Diagnosis
Accurate diagnosis requires visualization of the airway.
1. Flexible Bronchoscopy (Gold Standard)
Bronchoscopy is the most important investigation for diagnosing Subglottic Hemangioma.
- A reddish, compressible mass in the subglottic region
- Degree of airway narrowing
- Extent and exact location of the lesion
- Direct, real-time visualization
- Helps differentiate from other causes of stridor
- Minimally invasive and highly informative
2. Imaging Studies
- MRI with contrast helps confirm vascular nature and assess extent
3. Additional Evaluation
- Screening for associated syndromes (e.g., PHACE syndrome)
Treatment of Subglottic Hemangioma
1. Medical Management (First-Line)
Oral Propranolol
- Gold standard treatment
- Works by shrinking the hemangioma
- Leads to rapid improvement in symptoms
- High success rate
- Non-invasive
- Well tolerated under medical supervision
2. Systemic or Inhaled Steroids
- Used in selected cases
- Considered if propranolol is contraindicated
3. Endoscopic Interventions
- Laser therapy
- Microdebrider excision
4. Tracheostomy (Rare)
- Reserved for life-threatening airway obstruction
Importance of Early Diagnosis and Treatment
- Severe airway compromise
- Repeated hospitalizations
- Mismanagement as recurrent croup
Early use of bronchoscopy allows prompt diagnosis and timely initiation of treatment, significantly improving outcomes.
Conclusion
Subglottic Hemangioma is an important cause of progressive airway obstruction in young infants. Recognizing symptoms early and using bronchoscopy for diagnosis ensures timely treatment. With propranolol therapy, most infants achieve excellent outcomes.
Frequently Asked Questions (FAQs)
Frequently Asked Questions
1. What is the difference between subglottic hemangioma and croup?
Croup is usually viral and short-lived, while Subglottic Hemangioma causes progressive stridor and recurrent symptoms that do not resolve with standard treatment.
2. Is bronchoscopy necessary for diagnosis?
Yes, bronchoscopy is the most reliable way to confirm the diagnosis and assess airway obstruction.
3. Is propranolol safe for infants?
When prescribed and monitored by specialists, propranolol is safe and highly effective.
4. Can subglottic hemangioma go away on its own?
Yes, it regresses over time, but treatment is often required during the growth phase.
5. When should parents seek medical attention?
- Persistent or worsening stridor
- Breathing difficulty
- Recurrent croup-like episodes
Related conditions & services
Medical Advice & Clinical Disclaimer
The educational medical guidance provided in this guide is for informational purposes only. It should not be used as a substitute for direct pediatric consultation, physical diagnosis, or clinical prescription. For individualized medical assessment of your child, schedule an appointment with Dr. Ankit Parakh.